Warning
Only use this website if you have Gender Dysphoria/Gender Identity Disorder, a severe and rare medical condition. 1 2
Only read this guide if you are a transsexual man.
Hormonal replacement treatment is dedicated towards treating medical conditions, it is not a tool for personal aesthetics. That being said, this website and the maintainers are not responsible if you regret the usage of your hormonal treatment. Please make wise and future-considerate choices regarding your health.
This site has a moral obligation to warn of the risks towards your fertility if HRT is used. By staying long-term in effective ranges of testosterone, -WIP
Pink Pilling Advisory
“Pink Pilling” in this context, is a tactic of coercion with aims to convince others they are transgender. There are prevalent online communities that engage in this practice, specifically targeting the neurologically impaired, GNC children and questioning children. People who don’t need HRT at all. To learn more, please watch this video.
If you suspect you’re a victim of the following:
- Pressure to engage in “kinks” and online sexual conversations.
- Requests to do unwanted “truth or dares.”
- Coercion to undergo DIY HRT (Pink Pilling).
- Blackmail and online stalking.
Please refrain from reading this guide, leave those online communities and halt further contact with the perpetrators. Note there are endless depictions and representations of this manipulation, it’s an extensive topic that I can only attempt to summarize.
Being a masculine female or a feminine male does not make you trans.
Introductory
Please refrain from the usage of testosterone medication if you meet any of the contraindications listed below.
Transdermal testosterone products, non-standard testosterone esters and mixed esters will not be covered. Popular reasons against including such, but not limited to, was lack of available research, inconsistent pharmacokinetics between brands or large concentration variation.
Citation Guidelines
WIP As I’ve concluded in this article, I refuse to cite any research or academic bodies with direct involvement of the WPATH or their academics. Due to several major ethical, methodological and validity concerns. This includes the American Psychological Association.
All citations provided are sourced from empirical literature.
Timeline of Effects
This will take the longest. I’m planning a mass survey.
Adverse Reactions
WIP will write about soon.
Risks of Inappropriate Dosing
Contraindications
These are conditions that make administration of testosterone inadvisable.
WIP
General Guides
These are guides not directly related to testosterone hormone therapy but still offer fundamental information on being successful with DIY.
Administration How-To
Read our Master Guide on Injection.
It includes sources and plenty of sources to back up the claims.
Blood Tests How-To
Read our Master Guide on Blood Testing & Labs.
It includes sources and plenty of sources to back up the claims.
Obtain Testosterone
For Male HRT, we endorse two short esters of testosterone.
- Testosterone Enanthate
- Testosterone Cypionate
These are the only testosterone formulations you should buy.
Please be careful not to purchase 1-Testosterone Cypionate, also known as Dihydroboldenone. It’s named incredibly similar to Testosterone Cypionate but it’s actually a derivative of Dihydrotestosterone (DHT). Dihydroboldenone may also harm the liver, as it’s been shown to increase liver weight in rats. 3
Sources
This guide will not offer any information on sourcing testosterone, I have primarily three reasons as to why.
- It pushes this project into legal territory.
- Potentially violates hosting platforms Terms of Services.
- Conflates the DIY and bodybuilding ecosystems.
However I will advise you to be careful and research immensely, especially if you lack internet expertise. Several studies have shown substantial percentages of anabolic steroids (ie. testosterone) purchased from grey markets are fraudulent or of substandard quality. 4 5 According to Magnolini 2022, an estimated 36% of steroids are counterfeit and an additional 37% were of substandard quality. 6 Alongside accompanying literature exposing significant concentrations of heavy metals and microbial contamination that may harm user health. 7 8
Calculate Dosages
Upon obtaining a Testosterone vial, there will be text denoting the concentration. The text will appear as 250mg/mL or 2500mg/10mL.
This shows the amount of Testosterone (mg) within the total amount of oil (mL).
The most common concentration is 250mg/mL, which I’ll use as an example. Say you have a Testosterone vial that says “250mg/mL,” that means for every milliliter (mL) there is 250 milligrams (mg) of Testosterone. Vials tend to have 10mL of liquid. So if you multiply 250mg by 10, in reality the total concentration is 2500mg/10mL in the entire vial.
Learn to calculate dosages and vial life by yourself, try not to use AI or online dosage calculators. If you cannot responsibly dose for yourself, for your safety, do not DIY.
How to Calculate Dosage mL
[Dosage] / [Testosterone per mL] = [Syringe Millimeters]
50mg / 250mg = 0.2mL
If you wanted to dose 50mg and you had a 250mg/mL vial of Testosterone. You would divide 50mg by 250mg, then you’d get 0.2mL as the amount of liquid to draw inside your syringe for an injection of 50mg.
[Dosage] / [Testosterone per mL] = [Syringe Millimeters]
75mg / 200mg = 0.375mL
Another example, if you wanted to dose 75mg and you had a 200mg/mL vial of Testosterone. You would divide 75mg by 200mg, then you’d get 0.375mL as the amount of liquid to draw inside your syringe for an injection of 75mg.
How to Calculate Vial Life
In order to solve how long a vial could approximately last you, first, you must read this section on deadspace. Once completed, come back here to calculate.
Remember to convert deadspace, uL to mL, simply by multiplying the uL by 0.001. For example, 92uL is 0.092mL; 3uL is 0.003mL.
[Total mL] / ( [Dosage / Testosterone per mL] + [Total Deadspace] ) = [Injections per Vial]
10mL / ((50mg/250mg) + 92uL) = 34 Injections per Vial
If you have a 250mg/mL vial that has a total volume of 10mL, with a planned dosage of 50mg weekly alongside syringes with a deadspace of 92uL, this is how you would fill out the formula. This vial would last you about 34 injections, which would be 224 days if you were consistently injecting by a weekly basis.
[Total mL] / ( [Dosage / Testosterone per mL] + [Total Deadspace] ) = [Injections per Vial]
10mL / ((100mg/300mg) + 3uL) = 30 Injections per Vial
If you have a 300mg/mL vial that has a total volume of 10mL, with a planned dosage of 100mg weekly alongside syringes with a deadspace of 3uL, this is how you would fill out the formula. This vial would last you about 30 injections, which would be 210 days if you were consistently injecting by a weekly basis.
Recommended Regimens
We advise regular blood testing (every 6mos). Labs are not necessary in order to do DIY however they are essential to making educated adjustments to your regimen.
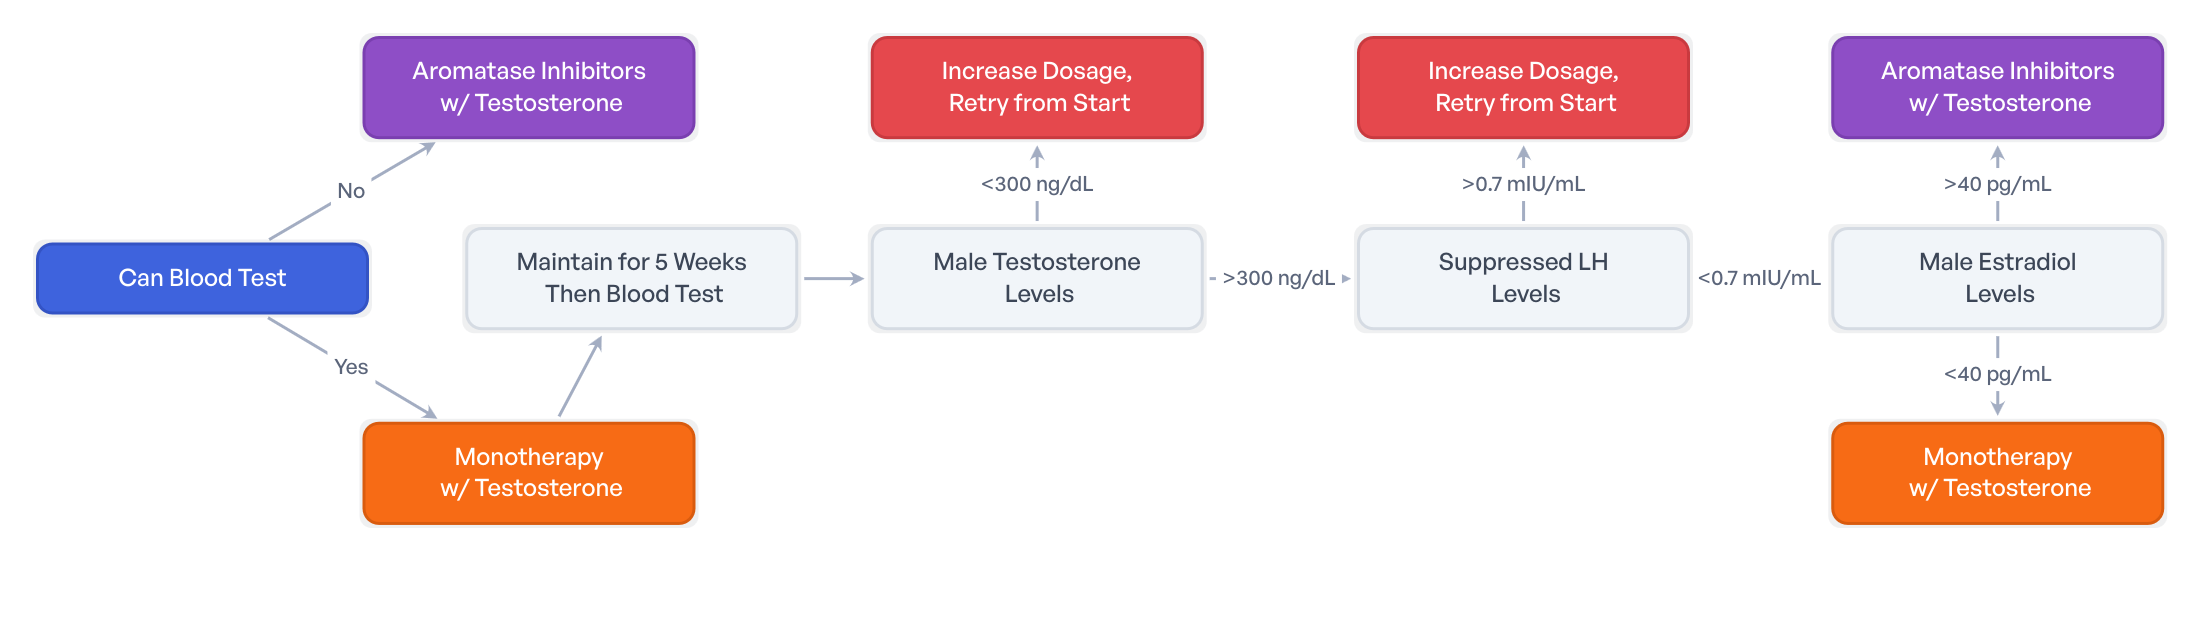
This website endorses two regimen types, monotherapy with short esters or aromatase inhibitors with short esters. Monotherapy means to take one medicine as treatment, which in this case is testosterone. We do not endorse underdosages, microdosing or any practice that is counteractive to virilization, as this guide is entirely purposed for men.
Here’s a flowchart on how to pick between both regimens.
Testosterone
I recommend reading this article for more studies on testosterone. (WIP)
Natal sex is not a controlling variable of interindividual variation, only what it may entail (ex. bodyweight). As men and women are equally androgen sensitive. 9 A person’s bodyweight is a major independent variable controlling for interindividual variation of testosterone pharmacokinetics. Pharmacokinetic parameters like clearance (CL) and volume (V) can vary 25% and 50% respectively by bodyweight. 10 Vogiatzi 2023 has demonstrated body weight’s affects in this testosterone enanthate simulation based for hypogonadal pediatric males. 11
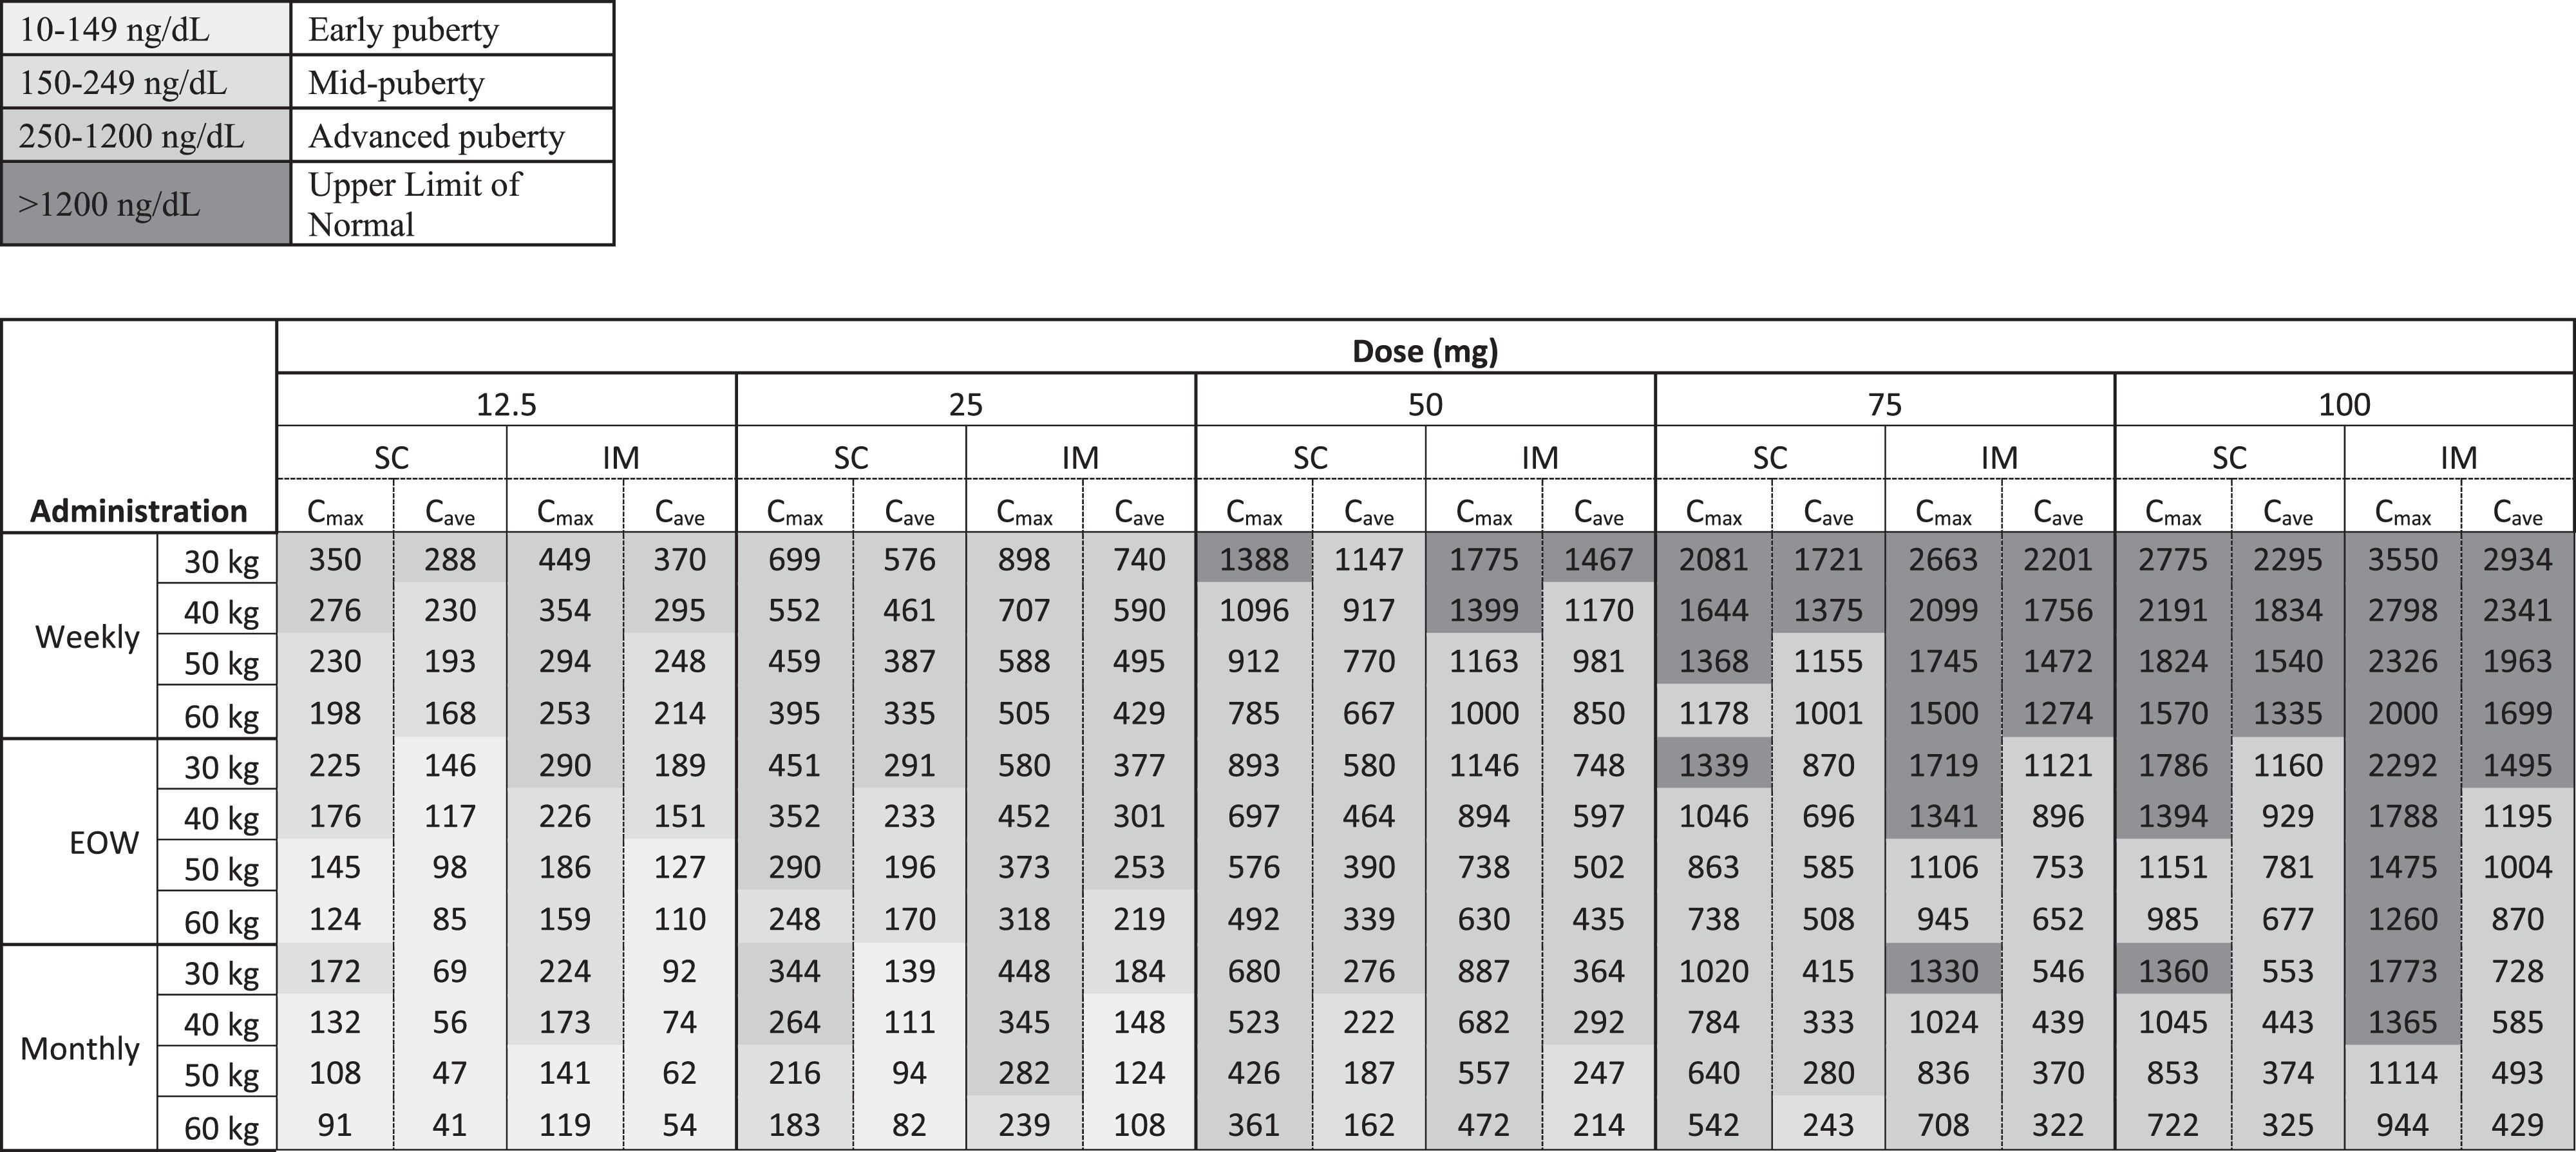
Looking at this graph, say you weigh 110 lbs (50 kg) and took 50mg SubQ weekly. You would average about 770 ng/dL of testosterone.
This table is primarily what these dosage recommendations are based upon. Each dosage should push testosterone levels within the 900-1200 ng/dL range, which are slightly above male physiological ranges of 264-916 ng/dL. 12 So why do I recommend this range for testosterone levels?
Three studies (Amory 2001, Borst 2014, Bi 2018), have shown men on TRT only reached gonadal suppression while taking 100mg or higher. For them, their trough levels averaged around 700 ng/dL. 13 However, 700 ng/dL is not enough for transsexual males to obtain gonadal suppression. From personal experience reading trans male labs, gonadal suppression is harder to achieve in TMs. While no study focused on TM ovarian suppression exists, a study on testosterone undecanoate has concluded the same. 14
“The present findings demonstrate that after individual dose titration, serum LH and FSH are markedly less suppressible in trans men compared with men with primary or secondary hypogonadism despite a higher dose in microgram per square meter.”
I’ve also decided to recommend 900-1200 ng/dL due to Bhasin 2001, a study consisting of five dosage cohorts, each taking 25mg, 50mg, 125mg, 300mg or 600mg of Testosterone Enanthate. 15 This study showed the men who took 25mg or 50mg had significant decreases in testosterone compared to baseline. It became so low, most could’ve been diagnosed with hypogonadism. As a result, they displayed traditional signs of hypogonadism like increased body fat and lack of ability to increase muscle volume and muscle mass. Whereas in the 125mg cohort, their body fat maintained alongside a significant increase in muscle volume and mass.
| < 50kg (110lbs) | 50kg-70kg (110lbs-155lbs) | > 70kg (155lbs) | N/A* |
|---|---|---|---|
| 50mg weekly | 75mg weekly | 100mg weekly | 125-150mg weekly |
* Denotes 125-150mg weekly may be taken, blood testing heavily advised prior to and after entering this range.
Aromatase Inhibitors
I recommend reading this article for more studies on aromatase inhibitors. (WIP)
Aromatase inhibitors (AIs) are a class of pharmaceuticals that target the enzyme Aromatase, which is responsible for the biosynthesis of the estrogens. Specifically, by converting certain androgens (ie. Testosterone) to estrogens (ie. Estradiol). 16 Estrogens are fundamentally important for normal human development, men included. 16
However, research has shown estrogen is generally outside of male reference ranges for trans men.
This revelation brought Greene 2021 to eventually conclude trans men shouldn’t share the same reference ranges as other men. Since only ~18% of their cohort would meet the <45 pg/mL reference interval. 17 Even this study (Chan 2018), cited 86 times, irrationally concluded there “appears to be no role for aromatase conversion inhibitors” in TM HRT treatment. Despite reporting an average baseline of 81 pg/mL to a staggering 54 pg/mL on testosterone. 18
I must clarify, estradiol concentrations like 54 pg/mL (Chan 2018) and >45 pg/mL (Greene 2021) are over 2 standard deviations compared to male estradiol levels. Which means, these populations had estrogen higher than 97.5% of men. 19
This is exactly indicative of why transsexuals don’t trust their doctors, it’s a reason why you shouldn’t. Academics prioritize traditional practices like monotherapy over advising actual solutions like aromatase inhibitors. They’re stuck in a dilemma between tradition and progress.
Please be aware you must have suppressed ovaries in order to take aromatase inhibitors. Loss of the estrogen negative feedback loop will actually increase the estrogens if the ovaries are still active. With that in mind, stick to 100mg - 125mg weekly. Potentially higher if you wish to take AIs.
Here’s my work in progress dosage table. I’ll update this once I read more research.
| Arimidex | Letrozole | Aromasin* |
|---|---|---|
| 0.5mg Daily | Do not take |
* Aromasin/Exemestane is irreversible, it binds to the enzymes until it’s turnover. It may nuke your estrogen for weeks, making it harder to adjust.
- ↩︎
- ↩︎
Friedel, A., Geyer, H., Kamber, M., Laudenbach-Leschowsky, U., Schänzer, W., Thevis, M., Vollmer, G., Zierau, O., & Diel, P. (2006). 17β-Hydroxy-5alpha-androst-1-en-3-one (1-testosterone) is a potent androgen with anabolic properties. Toxicology Letters, 165(2), 149–155. https://doi.org/10.1016/j.toxlet.2006.03.001 ↩︎
Câmara, L. C. (2023). Anabolic Androgenic Steroids from Underground Market: drug Quality and Implications for Research. Asian Journal of Research in Medical and Pharmaceutical Sciences, 12(3), 59–64. https://doi.org/10.9734/ajrimps/2023/v12i3221 ↩︎
Bonenti, B., Craven, A., Ferris, J., Walsh, C., Armstrong, M., & Piatkowski, T. (2026). Investigating the legitimacy of Anabolic-Androgenic steroids in Australia’s unregulated market using community testing data. Substance Use &Amp Addiction Journal, 47(3), 884–889. https://doi.org/10.1177/29767342261426103 ↩︎
Magnolini, R., Falcato, L., Cremonesi, A., Schori, D., & Bruggmann, P. (2022). Fake anabolic androgenic steroids on the black market – a systematic review and meta-analysis on qualitative and quantitative analytical results found within the literature. BMC Public Health, 22(1), 1371. https://doi.org/10.1186/s12889-022-13734-4 ↩︎
Pullirsch, D., Bellemare, J., Hackl, A., Trottier, Y., Mayrhofer, A., Schindl, H., Taillon, C., Gartner, C., Hottowy, B., Beck, G., & Gagnon, J. (2014). Microbiological contamination in counterfeit and unapproved drugs. BMC Pharmacology and Toxicology, 15(1), 34. https://doi.org/10.1186/2050-6511-15-34 ↩︎
Craven, A., Ferris, J., Nielsen, S., & Piatkowski, T. (2025). Lead astray? The hidden contaminants in Australian Anabolic–Androgenic steroid market and their potential health impact. Drug and Alcohol Review, 44(6), 1641–1647. https://doi.org/10.1111/dar.70007 ↩︎
Handelsman, D. J., Hirschberg, A. L., & Bermon, S. (2018). Circulating testosterone as the hormonal basis of sex differences in athletic performance. Endocrine Reviews, 39(5), 803–829. https://doi.org/10.1210/er.2018-00020 ↩︎
Bi, Y., Perry, P. J., Ellerby, M., & Murry, D. J. (2018). Population Pharmacokinetic/Pharmacodynamic Modeling of Depot testosterone cypionate in healthy male subjects. CPT Pharmacometrics & Systems Pharmacology, 7(4), 259–268. https://doi.org/10.1002/psp4.12287 ↩︎
Vogiatzi, M. G., Jaffe, J. S., Amy, T., & Rogol, A. D. (2023). Allometric scaling of testosterone Enanthate pharmacokinetics to adolescent hypogonadal males (IM and SC Administration). Journal of the Endocrine Society, 7(6), bvad059. https://doi.org/10.1210/jendso/bvad059 ↩︎
Travison, T. G., Vesper, H. W., Orwoll, E., Wu, F., Kaufman, J. M., Wang, Y., Lapauw, B., Fiers, T., Matsumoto, A. M., & Bhasin, S. (2017). Harmonized reference ranges for circulating testosterone levels in men of four cohort studies in the United States and Europe. The Journal of Clinical Endocrinology & Metabolism, 102(4), 1161–1173. https://doi.org/10.1210/jc.2016-2935 ↩︎
Narayana, N. S., Ly, L. P., Jayadev, V., Fennell, C., Savkovic, S., Conway, A. J., & Handelsman, D. J. (2021). Optimal injection interval for testosterone undecanoate treatment of hypogonadal and transgender men. Endocrine Connections, 10(7), 758–766. https://doi.org/10.1530/ec-21-0109 ↩︎
Bhasin, S., Woodhouse, L., Casaburi, R., Singh, A. B., Bhasin, D., Berman, N., Chen, X., Yarasheski, K. E., Magliano, L., Dzekov, C., Dzekov, J., Bross, R., Phillips, J., Sinha-Hikim, I., Shen, R., & Storer, T. W. (2001). Testosterone dose-response relationships in healthy young men. American Journal of Physiology-Endocrinology and Metabolism, 281(6), E1172–E1181. https://doi.org/10.1152/ajpendo.2001.281.6.e1172 ↩︎
Hamilton, K. J., Hewitt, S. C., Arao, Y., & Korach, K. S. (2017). Estrogen Hormone Biology. In Current topics in developmental biology/Current Topics in Developmental Biology (Vol. 125, pp. 109–146). https://doi.org/10.1016/bs.ctdb.2016.12.005 ↩︎ ↩︎
Greene, D. N., Schmidt, R. L., Winston-McPherson, G., Rongitsch, J., Imborek, K. L., Dickerson, J. A., Drees, J. C., Humble, R. M., Nisly, N., Dole, N. J., Dane, S. K., Frerichs, J., & Krasowski, M. D. (2020). Reproductive Endocrinology Reference Intervals for Transgender men on stable hormone therapy. The Journal of Applied Laboratory Medicine, 6(1), 41–50. https://doi.org/10.1093/jalm/jfaa169 ↩︎
Chan, K. J., Jolly, D., Liang, J. J., Weinand, J. D., & Safer, J. D. (2018). Estrogen levels do not rise with testosterone treatment for transgender men. Endocrine Practice, 24(4), 329–333. https://doi.org/10.4158/ep-2017-0203 ↩︎
Frederiksen, H., Johannsen, T. H., Andersen, S. E., Albrethsen, J., Landersoe, S. K., Petersen, J. H., Andersen, A. N., Vestergaard, E. T., Schorring, M. E., Linneberg, A., Main, K. M., Andersson, A., & Juul, A. (2019). Sex-specific Estrogen Levels and Reference Intervals from Infancy to Late Adulthood Determined by LC-MS/MS. The Journal of Clinical Endocrinology & Metabolism, 105(3), 754–768. https://doi.org/10.1210/clinem/dgz196 ↩︎